Blog / General Medicare
📋 General Medicare
By Mike Miligi, Certified Medicare Insurance Planner- Michael M Insurance Services
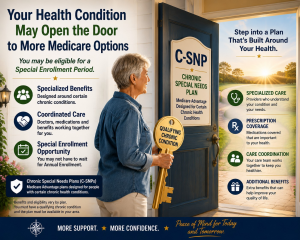
If you’re managing diabetes, heart failure, COPD, or another serious ongoing condition, there’s a category of Medicare Advantage plan built specifically around that reality: the Chronic Condition Special Needs Plan, or C SNP. Most people never hear about it during Annual Enrollment because it isn’t available to everyone — but for the people it is available to, it can mean a formulary built around their actual medications, a required care coordinator, and enrollment flexibility no standard plan offers. Here’s exactly how it works for 2026.
A Chronic Special Needs Plan (C-SNP) is a type of Medicare Advantage plan restricted to people with a documented, severe chronic condition. Instead of serving the general Medicare population, a C-SNP builds its provider network, drug formulary, and care coordination specifically around managing one or more qualifying
conditions.
Like every Medicare Advantage plan, a C-SNP is offered by a private insurer approved by Medicare and is required by law to cover everything Original Medicare covers. What changes is who can enroll and what gets built on top of that baseline coverage.
CMS defines 15 chronic condition categories under 42 CFR 422.2 that a C-SNP is permitted to serve. A plan
may be built around a single condition, a CMS-approved grouping of related conditions, or several at once:
If your condition doesn’t fall into one of these categories — or no plan serving your category is available where
you live — a C-SNP simply isn’t an option, no matter how serious the condition is
Getting into a C-SNP is only step one. Once you enroll, your doctor typically has 60 days from your coverage start date to submit a form verifying your qualifying condition. Miss that window, and you can be involuntarily disenrolled — which is why it’s worth calling your doctor’s office the same week you enroll, not weeks later.
Every C-SNP is also required to build a personalized care plan for each member, often with a dedicated care coordinator managing appointments across your specialists. That’s a level of coordination standard Medicare Advantage plans aren’t required to offer.
Beyond standard Part A and Part B services, every C-SNP is required to include Part D prescription drug coverage — it’s never optional, unlike some standard Medicare Advantage plans. Formularies are typicalllly weighted toward the medications used to manage your qualifying condition, which is often where the real savings show up.
Many C-SNPs also offer Special Supplemental Benefits for the Chronically Ill (SSBCI) — extra benefits tied directly to your condition, which can include:
Not every plan offers every SSBCI benefit, and eligibility is confirmed against specific plan criteria — never assume a benefit applies just because you qualify for the plan itself
Many C-SNPs carry a $0 monthly plan premium, similar to standard Medicare Advantage plans. You’ll still pay the standard Part B premium ($202.90/month in 2026 for most people). Some plans have a $0 medical deductible, and the maximum Part D deductible is capped at $615 for 2026.
The number worth paying attention to is the out-of-pocket maximum (MOOP). Every plan caps annual out-of pocket spending — in 2026, the ceiling is $9,250 for in-network care. Original Medicare has no such cap at all.
Prescription costs get an added layer of protection: the $2,100 annual out-of-pocket cap on Part D drug costs continues in 2026. Once you hit that number, your plan covers 100% of drug costs for the rest of the year — a meaningful protection if you’re managing a condition with ongoing prescription needs.
Picture two people with type 2 diabetes in the same county. One enrolls in a standard Medicare Advantage plan with a general for mulary. The other enrolls in a C-SNP built around diabetes, with a for mulary weighted toward insulin and related supplies, plus a $0 copay tier for those specific medications.
In a year with stable, well-managed care, the difference might just be lower monthly drug costs. But add a hospitalization, a new specialist, or a medication change, and the C-SNP’s required care coordinator — the person tracking referrals, appointments, and prescriptions across providers — is the difference between a
smooth handoff and a dropped ball. That coordination isn’t guaranteed on a standard plan; it’s required on a C SNP.
Unlike most Medicare Advantage enrollment, which is limited to specific windows, C-SNPs come with a Chronic Condition Special Enrollment Period (SEP). If you have a qualifying condition and a C-SNP serving it is available in your area, you can enroll any time during the year — not just during Annual Enrollment (October 15 – December 7).
You can also enroll during:
C-SNP availability varies significantly by county and can change year to year — it’s never safe to assume one exists where you live. If nothing serving your condition is currently offered, a standard Medicare Advantage plan with strong chronic-condition support, or a Medicare Supplement plan, may still serve you well. It’s worth confirming directly rather than guessing, and revisiting availability at the next Annual Enrollment Period, since it can change.
One more thing worth knowing: a C-SNP cannot be combined with a Medigap policy, the same as any Medicare Advantage plan. If you’re currently on Original Medicare with Medigap and considering a switch, that’s a decision worth thinking through carefully — especially since getting a Medigap policy back later isn’t guaranteed in most states if your health has changed.
Often yes, if one is available in your area. Because the formulary is built around medications for your specific condition, you may see meaningfully lower or $0 copays on the drugs you’re already taking, plus a required care coordinator managing referrals and appointments across your specialists — a level of coordination
standard Medicare Advantage plans aren’t required to provide. The catch is availability: not every county has a C-SNP for every condition, so that’s the first thing to confirm before comparing costs.
Your doctor typically has 60 days from your coverage start date to submit verification of your qualifying condition. If that window passes without verification, CMS allows the plan to involuntarily disenroll you — and you’d need to find alternative coverage, potentially outside a normal enrollment window. This is the single most
common way people accidentally lose C-SNP coverage, so it’s worth calling your doctor’s office the same week you enroll rather than assuming the paperwork will get filed automatically.
Yes, generally. The Chronic Condition Special Enrollment Period (SEP) is available any time you have adocumented qualifying condition, as long as a C-SNP serving that condition is actually offered where you liveand you don’t already have a C-SNP for it. This is different from most Medicare Advantage enrollment, which isrestricted to Initial Enrollment, Annual Enrollment (October 15 – December 7), or a handful of other qualifying SEPs.
A C-SNP serves people with a qualifying chronic condition, regardless of income or Medicaid status. A D-SNP (Dual Special Needs Plan) serves people who qualify for both Medicare and Medicaid, regardless of health condition. The two aren’t mutually exclusive — someone managing diabetes who also qualifies for Medicaid could be eligible for either type, and in that case, it’s worth comparing both directly rather than assuming one is automatically the better fit
Not necessarily. Many C-SNPs carry a $0 monthly premium, same as standard Medicare Advantage plans, and you’ll still pay the standard Part B premium either way ($202.90/month in 2026 for most people). Where the real difference shows up is prescription costs: because the formulary is weighted toward your qualifying condition’s medications, you may see reduced or $0 copays on drugs that would carry standard cost-sharing on a general Medicare Advantage formulary. Over a year of ongoing prescriptions, that difference can add up to hundreds of dollars even with an identical monthly premium.
Yes, in some cases. Plans may require periodic re-verification of your qualifying condition, not just the initial 60 day check. If your condition no longer meets the qualifying criteria — for example, a condition goes into sustained remission — you may need to transition to a different plan. The plan is required to notify you in writing and help manage that transition, but it’s worth knowing this isn’t a one-time check you pass and forget about.
It can work in your favor. A C-SNP can be built around a single condition, a CMS approved grouping of related conditions, or several conditions at once. If you manage more than one qualifying condition (for example, diabetes and cardiovascular disease), you may have more plan options available, since you’d qualify under multiple condition categories rather than just one. It’s worth mentioning every diagnosed condition when reviewing options, not just the one you consider primary.
No, and this is one of the most common misconceptions. Special Supplemental Benefits for the Chronically Ill (SSBCI) are optional benefits that individual plans choose whether to offer, and eligibility for each one is confirmed against specific criteria in the plan’s Evidence of Coverage — not assumed automatically just because you’re enrolled in the C-SNP itself. Two C-SNPs built around the same condition, even in the same county, can offer very different SSBCI benefits. Always ask which specific benefits a plan includes before assuming they’re all there
C-SNP availability varies significantly by county and can change from one year to the next, so it’s never safe to assume based on general information. If nothing serving your condition is currently offered in your area, a standard Medicare Advantage plan with strong chronic-condition support, or a Medicare Supplement plan, may still be the better available option. It’s also worth revisiting at the next Annual Enrollment Period, since new C SNPs do get added to counties over time.
It depends on the plan’s network structure, the same as any Medicare Advantage plan — C-SNPs aren’t automatically more or less restrictive than standard plans in this respect. Some are HMO-structured and require referrals for specialist visits, while others operate more like a PPO. Since a C-SNP is specifically built around managing a chronic condition that likely involves multiple specialists, it’s worth confirming referral rules and specialist network access before enrolling, not after.
Yes. You can generally switch during Annual Enrollment like any Medicare Advantage plan, and depending on your situation, you may also qualify for a Special Enrollment Period — for example, if you develop a different qualifying condition, or if you no longer meet your current plan’s criteria. If you’re dropping a C-SNP to return to Original Medicare, keep in mind that picking up a Medigap policy afterward isn’t guaranteed to be available at standard rates in most states if your health has changed since your original Medicare eligibility.
C-SNPs are one of the more overlooked corners of Medicare, mostly because they only apply to a subset of people — but for those they apply to, getting it right can mean real savings and meaningfully better care coordination. If you’re managing a chronic condition and want to know whether a C-SNP is available where you live, or how it stacks up against your current coverage, give me a call. That conversation is always free



